
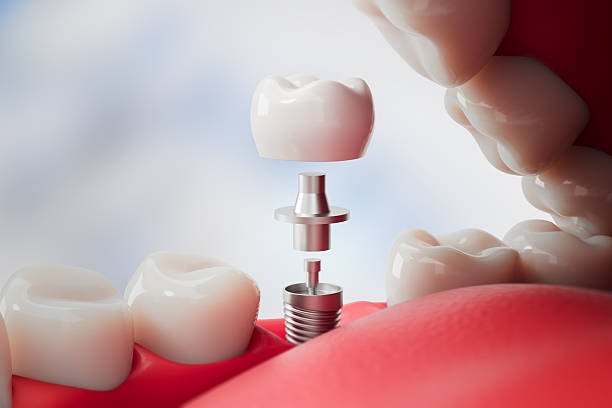
Fibrous encapsulation happens when connective tissue forms between a dental implant and the surrounding jawbone instead of the direct bone-to-implant contact that stable healing requires. Rather than fusing solidly with bone, the implant becomes surrounded by a layer of soft, fibrous tissue that cannot provide the same rigid support.
Several factors can contribute to this outcome, including poor primary stability at placement, excessive micromovement during healing, premature loading, low bone density, infection, surgical trauma, or unfavorable conditions at the implant site. A fibrous interface does not anchor an implant as effectively as bone, and the implant may remain mobile as a result. This usually represents a form of failed osseointegration, which differs from peri-implantitis, a condition that generally affects an implant that integrated successfully at first. Because a loose crown or screw can feel similar to a mobile implant fixture, an accurate diagnosis requires a professional evaluation rather than guesswork at home, and future implant treatment may still be possible once the site is properly managed. If your implant does not feel the way it should, a dental implant evaluation in New London, CT can help identify what your dental implant treatment options may include.
Key Takeaways
- Fibrous encapsulation means connective tissue formed between the implant and bone instead of stable osseointegration.
- Excessive movement during healing is an important contributing factor, though not the only one.
- Poor implant stability, infection, bone quality, and premature loading can all affect how well an implant integrates.
- A fibrously encapsulated implant may be mobile and unable to support predictable chewing forces.
- Retreatment may still be possible after the failed implant is removed and the site is properly evaluated.
What Is Fibrous Encapsulation Around a Dental Implant?
A dental implant depends on direct structural contact with bone, rather than soft tissue between the implant and bone, to function like a natural tooth root. Fibrous encapsulation means that normal bone connection did not form predictably, a pattern often described as failed implant integration.
Healthy Dental Implants Develop Direct Bone-to-Implant Contact
During normal healing, living bone grows directly against the implant surface. This process, known as osseointegration, creates true bone-to-implant contact and supports biological implant stability. Bone continues to remodel around the implant in the months after placement, gradually strengthening implant integration.
Fibrous Tissue Can Form When Stable Bone Integration Does Not Develop
When healing does not progress this way, fibrous encapsulation can occur: a layer of fibrous connective tissue forms around the implant instead of bone. This tissue is more flexible than bone, so it cannot rigidly anchor the implant surface. Normal chewing forces can then create movement at this interface, leading to failed bone integration rather than a stable, load-bearing connection.
Fibrous Encapsulation Is Different From Normal Gum Tissue Around the Implant
It helps to separate two different tissue areas. Healthy gum tissue naturally surrounds the upper portion of an implant, forming a soft-tissue seal near the surface. Fibrous encapsulation is a separate issue that occurs deeper, at the implant-bone interface, where bone is supposed to provide firm anchorage.
How Does Fibrous Encapsulation Develop During Implant Healing?
Healing after implant placement moves through mechanical and biological stages. Fibrous encapsulation tends to develop when something interrupts that sequence.
Primary Stability Holds the Implant Still Before Biological Integration Develops
Primary stability is the mechanical grip an implant has on bone immediately after placement, before any biological healing has occurred. It depends on bone density, bone volume, implant diameter, implant length, implant shape, thread design, implant position, and how the osteotomy site was prepared. Strong primary stability gives bone the calm environment it needs to begin forming a lasting connection.
Bone Remodeling Temporarily Changes Implant Stability During Healing
As healing progresses, bone around the osteotomy site remodels, and stability gradually shifts from a purely mechanical hold toward secondary stability, the biological anchorage that develops as new bone forms against the implant. This transition period is sensitive, since the implant relies less on mechanical grip and has not yet built full secondary stability. Disruptions during this window are more likely to affect how bone forms.
Excessive Micromovement Can Disrupt Bone Formation
Micromovement refers to small, repeated shifts between the implant and surrounding tissue during healing. It can come from inadequate primary stability, premature chewing pressure, immediate loading in a situation not suited for it, a loose temporary prosthesis, bruxism, uneven occlusal contacts, full-arch loading problems, or in some cases, functional forces from the tongue. According to NIDCR-supported research, implants can fail to properly integrate with bone when they experience too much physical stress during healing. When movement exceeds what healing tissue can tolerate, bone formation may be disrupted, and fibrous tissue can develop in its place.
What Causes Fibrous Encapsulation Around a Dental Implant?
Fibrous encapsulation usually results from several interacting risk factors rather than one isolated cause.
Poor Primary Implant Stability
Inadequate mechanical stability at placement increases the chance of disruptive movement during healing. Contributors can include low-density bone, a large extraction socket, limited cortical bone engagement, insufficient bone volume, an oversized osteotomy relative to the implant, an implant design that doesn’t suit the site, or an implant that does not match the site’s dimensions. Research on primary stability and osseointegration points to secure mechanical stability as an important factor in successful, long-term implant integration.
Excessive Micromovement During Early Healing
Micromovement affects healing through a fairly direct chain: movement at the implant-bone interface creates tissue instability, and that instability interferes with the cells responsible for direct bone formation. Without that bone formation, a fibrous interface can take hold instead. This relationship helps explain why controlling movement during the healing window matters as much as achieving good stability at placement. The exact point at which movement becomes disruptive varies by patient and site.
Premature Loading Before the Implant Is Ready
There is an important difference between planned immediate loading, which is deliberately timed and monitored, and uncontrolled premature loading from heavy temporary crown contacts or full-arch bridge forces. Immediate loading itself is not inherently problematic when it is appropriately planned. Problems tend to arise when an implant faces functional force before it has adequate stability to handle it.
Poor Bone Density or Bone Quality
Bone quality depends partly on the balance between cortical bone, the dense outer layer, and trabecular bone, the softer, more porous bone underneath. Areas like the posterior maxilla often have less cortical density and a more open trabecular architecture, which can provide less mechanical engagement for an implant. This does not automatically mean an implant will fail, but it is a factor that periodontists weigh carefully during planning and site evaluation.
Infection During the Early Healing Period
Existing infection, bacterial contamination, wound breakdown, or poor plaque control can disrupt healing and interfere with bone formation around an implant. Possible signs include swelling, drainage, persistent pain, a bad taste, or redness near the site. Infection and fibrous encapsulation are related but not identical concepts, since infection is one possible contributor rather than a guaranteed outcome.
Surgical Trauma to the Surrounding Bone
Bone needs to remain biologically viable after implant placement. Excessive heat during drilling, overcompression, traumatic preparation of the osteotomy, thin bone walls, or a compromised blood supply can all affect bone’s ability to heal properly around the implant.
Smoking and Nicotine Exposure
Smoking and nicotine exposure can affect blood supply, oxygen delivery, and the body’s healing response. These effects may influence both bone healing and soft tissue healing around a dental implant, though outcomes vary from patient to patient.
Medical Conditions That Affect Healing
Poorly controlled diabetes, immune compromise, certain medications that affect bone remodeling, and a history of radiation can all influence healing. These conditions act as risk modifiers rather than automatic reasons why an implant cannot succeed.
What Does Fibrous Encapsulation Feel Like?
Symptoms vary from patient to patient, and some cases do not cause dramatic signs at all.
The Implant Fixture May Feel Mobile
True movement of the implant fixture itself, not just the crown, the abutment, or the retaining screw, is a significant clinical finding. A loose screw, an abutment that has come loose, or a shifting crown can all mimic implant mobility without indicating a problem with the fixture itself. If you have noticed movement, our article on why an implant may feel loose explains this symptom in more depth.
Chewing May Feel Unstable or Uncomfortable
Some patients notice pressure, movement, clicking, an uneven bite, or an unusual sensation when biting down. These sensations can also come from prosthetic components rather than the implant itself, which is part of why professional evaluation matters.
Pain May Persist—or There May Be Very Little Pain
Failed integration does not always cause severe pain, and painless implant failure is more common than many patients expect. Some implants feel uncomfortable, while others show very little discomfort and are identified mainly through mobility found during a professional exam, not through pain at all.
Swelling or Signs of Infection May Be Present in Some Cases
Swelling, drainage, redness, a bad taste, or persistent tenderness can point toward inflammation or infection. These signs are not unique to fibrous encapsulation, but they are always worth having evaluated.
How Is Fibrous Encapsulation Different From Failed Osseointegration?
These two terms are related, but they describe different levels of the same problem.
Failed Osseointegration Describes the Overall Failure to Achieve Stable Bone Integration
Failed osseointegration is a broad outcome that can result from several different mechanisms. Our article on why an implant may fail to fuse with the jawbone covers the range of reasons why this can happen.
Fibrous Encapsulation Describes the Tissue That Forms Instead of Stable Bone Contact
Fibrous encapsulation is one specific biological pattern that can occur when osseointegration fails. In other words, failed osseointegration may involve a fibrous connective tissue interface, but not every case of failed integration looks identical under the surface.
How Is Fibrous Encapsulation Different From Peri-Implantitis?
Patients sometimes confuse these two conditions, but they develop under very different circumstances.
Fibrous Encapsulation Usually Develops During Initial Healing
Fibrous encapsulation reflects an implant that never achieved stable integration in the first place. Mobility, when present, tends to appear early, often before the final restoration is placed.
Peri-Implantitis Usually Affects an Implant That Previously Integrated
Peri-implantitis is a bacterial, inflammatory condition that affects an implant that originally integrated with bone successfully. It involves progressive bone loss, bleeding, and sometimes suppuration, and any mobility tends to develop later, after a period of normal function.
How Does a Periodontist Diagnose Fibrous Encapsulation?
There is no safe way to test implant mobility at home. Diagnosis relies on a combination of history, clinical exam, and imaging.
Reviewing the Implant Healing Timeline
A periodontist starts by reviewing when the implant was placed, how it was loaded, what type of temporary restoration was used, and when any symptoms began. Prior infection, bone grafting history, smoking, medical conditions, any history of trauma to the area, and bruxism all factor into this picture.
Determining Whether the Implant Fixture Is Actually Mobile
The exam distinguishes between movement in the crown, screw, or abutment and true movement of the implant fixture within bone. This distinction matters, since a loose restoration is a very different problem from a non-integrated implant.
Evaluating the Surrounding Gum Tissue
The periodontist also checks for redness, swelling, bleeding, drainage, and how well the surrounding tissue has healed. Pocket formation around the implant can offer additional clues.
Using X-Rays to Evaluate Bone Around the Implant
Standard X-rays support dental implant bone evaluation by showing radiolucency, a dark area that can signal reduced or missing bone contact, along with marginal bone levels and implant position. Comparing these images against earlier X-rays helps track whether anything has changed over time.
CBCT Imaging When Three-Dimensional Evaluation Is Needed
When a more detailed view is needed, CBCT imaging provides a three-dimensional look at remaining bone, any defects, the facial and lingual bone walls, and the implant’s position relative to nearby anatomy. This level of detail is often useful for planning retreatment if it becomes necessary.
Implant Stability Measurements May Support the Diagnosis
Tools such as resonance frequency analysis can measure an implant stability quotient, giving an objective read on how firmly an implant is anchored. No single measurement proves fibrous encapsulation on its own. A periodontist combines these results with a clinical mobility assessment and imaging to reach a diagnosis.
Can a Dental Implant With Fibrous Encapsulation Still Integrate Later?
A truly mobile implant surrounded by fibrous tissue is generally not considered predictably osseointegrated. Continuing to place normal chewing forces on it can maintain that movement, prevent stable bone healing, and increase damage to the surrounding tissue. Once significant failed integration has been confirmed, waiting indefinitely in hopes that a mobile implant will stabilize on its own is generally not a predictable approach to treatment.
Can Fibrous Encapsulation Be Treated Without Removing the Implant?
The right path depends on one key diagnostic question: is the implant fixture itself stable, or is only the crown, abutment, or screw moving? The answer determines whether the situation calls for a simple repair or a more involved treatment plan.
A Loose Crown or Abutment May Be Repairable Without Removing the Implant
If the implant fixture itself is stable and the issue is a loose or worn crown, a loose screw, a worn abutment, or a bite that needs adjustment, these components can often be repaired, tightened, or replaced without disturbing the implant. This scenario is not fibrous encapsulation.
A Truly Mobile Non-Integrated Implant Usually Requires a Different Treatment Path
When the implant fixture itself has not developed stable bone integration, removal is often considered. The goal at that point shifts to preserving remaining bone, removing any fibrous or infected tissue, evaluating the defect, determining whether grafting will be needed, and planning what comes next.
What Happens After a Fibrously Encapsulated Implant Is Removed?
Removal is not the end of treatment. It is the start of preparing the site for what may come next.
The Implant Site Is Carefully Evaluated
The periodontist examines the remaining bone, the shape of the defect, and any signs of infection or unhealthy tissue to understand what led to the original failure.
Fibrous or Inflamed Tissue May Need to Be Removed
Any fibrous or inflamed tissue is typically removed to create a healthier environment for future healing.
Bone Grafting May Be Recommended
If bone walls were damaged, previous infection led to bone loss, or the implant removal itself leaves a defect, bone grafting may be recommended to support implant site regeneration and rebuild ridge volume before another implant is considered.
The Site May Need Time to Heal Before Another Implant
Healing time varies based on the size of the defect, whether infection was present, whether grafting was performed, the quality of the remaining bone, and each patient’s overall tissue and medical health. There is no single timeline that applies to every case.
Can Another Dental Implant Be Placed After Fibrous Encapsulation?
In many cases, yes, once the original cause has been identified and addressed.
Why Identifying the Cause of the First Failure Matters
Correcting the issues behind the first failure, whether that involves stability, bone density, implant position, implant dimensions, premature loading, infection, smoking, bruxism, or an underlying medical risk factor, gives a second attempt a better foundation.
The Replacement Implant May Need a Different Treatment Plan
A replacement implant may call for a different diameter, length, or position, additional bone grafting, guided placement, a longer healing period, delayed loading, bite protection, or a different temporary restoration strategy. Each of these adjustments is based on what the evaluation reveals about the original site.
How Can the Risk of Fibrous Encapsulation Be Reduced?
No approach can guarantee a specific healing outcome, but several steps can help reduce risk.
Achieving Adequate Primary Stability
Careful bone evaluation, surgical planning, thoughtful implant selection based on the right dimensions and design, and proper site preparation all contribute to solid primary stability from the start.
Limiting Excessive Implant Movement During Healing
A well-designed loading protocol, a properly fitted temporary restoration, bite adjustment, and clear postoperative instructions all help protect the implant while healing progresses.
Evaluating Bone Density and Volume Before Placement
Thorough evaluation of bone density and ridge dimensions before placement, sometimes supported by CBCT imaging, along with grafting when appropriate, helps set realistic expectations and supports better outcomes.
Managing Infection Before and After Implant Placement
Treating periodontal disease, addressing any extraction-site infection, maintaining good oral hygiene, and following up with professional monitoring all support healthy integration.
Addressing Bruxism and Excessive Bite Forces
For patients who grind or clench, occlusal analysis, a protective appliance where appropriate, and careful force control across a full-arch restoration can all help limit excessive force on a healing implant.
Frequently Asked Questions About Fibrous Encapsulation and Dental Implants
What does fibrous encapsulation mean in dental implants?
It means fibrous connective tissue formed between the implant and bone instead of the stable, direct bone contact that healthy healing requires.
Is fibrous encapsulation the same as failed osseointegration?
Fibrous encapsulation can be one mechanism or tissue outcome associated with failed osseointegration, but the two terms are not perfectly interchangeable.
What causes fibrous tissue to form around a dental implant?
Poor stability, excessive movement, premature loading, infection, poor bone quality, or impaired healing can all contribute.
Can fibrous encapsulation cause a loose dental implant?
Yes. A fibrous interface cannot provide the same rigid stability that osseointegrated bone offers.
Does fibrous encapsulation cause pain?
It may, but some failed implants remain mobile without causing severe pain.
Can fibrous encapsulation be seen on an X-ray?
Imaging may show reduced or abnormal bone contact, but an accurate diagnosis combines imaging with clinical stability testing and a tissue exam.
Can a fibrously encapsulated implant be saved?
A truly mobile, non-integrated fixture is generally not considered predictably functional, though the exact path forward depends on individual clinical findings.
Does the implant have to be removed?
Removal may be recommended once failed integration is confirmed and the implant remains mobile.
Can another implant be placed after fibrous encapsulation?
In many cases, yes, after identifying the cause, treating the site, restoring bone when necessary, and allowing appropriate healing.
How can fibrous encapsulation be prevented?
Risk can be reduced through careful implant planning, strong primary stability, force control during healing, infection management, and a healing protocol suited to each patient.
Schedule an Evaluation for a Dental Implant That Is Not Healing Properly in New London, CT
If you have noticed implant movement, persistent pain, discomfort when chewing, swelling, drainage, an unusual taste, healing that seems to be taking longer than expected, or a restoration that no longer feels secure, it is worth having the site evaluated rather than waiting to see if it resolves on its own. At Shoreline Periodontics & Dental Implants, our New London, CT team can assess implant stability, check for movement in the crown, abutment, or fixture, evaluate bone-to-implant support and bone quality, and look for signs of infection or failed osseointegration using X-rays and CBCT imaging when needed. If a problem is identified, we can walk you through what removal, bone grafting, and future replacement options may look like for your specific situation. We also see patients from Middletown, CT, and Westerly, RI who want a clear, honest assessment of a dental implant that does not feel the way it should.
